

This is the Weight and Healthcare newsletter! If you like what you are reading, please consider subscribing and/or sharing!
In Part 1 we looked at the basics of a study that compared the two newest GLP-1 weight loss drugs against each other - Novo Nordisk’s Semaglutide (Wegovy) and Eli Lilly’s Tirzepatide (Zepbound) The trial was funded by Eli Lilly and while many of the authors took money from the makers of both drugs, the only authors (some of whom were statisticians) who were employed by and owned stock in a drug company were from Eli Lilly. While that isn’t proof of bias, it’s certainly a red flag.
Today we’ll look at the study and its findings. Quotes from the study itself are indented and contain weight stigma and what I would characterize as misleading claims. You can skip those sections and still get the gist of what I’ve written.
As always, I take a firm view of bodily autonomy and I would never shame/blame anyone for choosing to try these drugs. My focus is patient’s right (and provider’s obligation) to the ethical, evidence-based practice of medicine, including informed consent and accurate information about the drugs.
As a reminder, this was a 72 week study with half the participants taking high-dose tirzepatide (10mg or 15mg) and half taking high-dose semaglutide (1.7mg or 2.4mg) that measured weight loss and waist circumference.
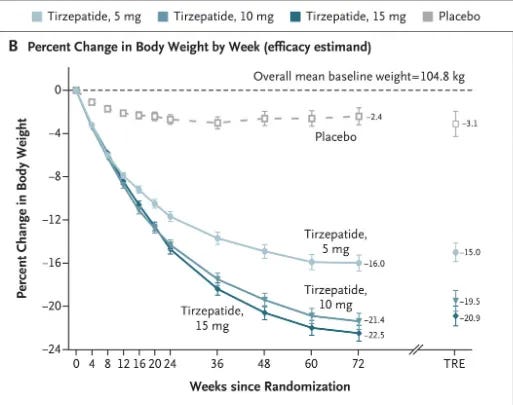
One thing I want to point out here is that one bit of push-back that I often get when I talk about the mega-doses of these drugs that are used for weight loss (as opposed to the often lower doses used for type 2 diabetes) is that people don’t have to take the highest doses. While that’s true, it is also true that the research only looks at the highest doses. Early tirzeptide studies for weight loss included the 5mg dose which showed (at least short term) weight loss of about 16% (which is well over the questionable 5-10% they claim is “clinically meaningful) and yet they dropped that dose in subsequent trials, including this one.
Here, in their own words, is how this particular sausage was made:
The sponsor (Eli Lilly) and the first two authors designed the trial. The trial-site investigators were responsible for data collection, and the sponsor undertook site monitoring, data collation, and data analysis. The first draft of the manuscript was written by the first and last authors. The investigators worked under confidentiality agreements with the sponsor. All the authors participated in the interpretation of the data and the critical review of the manuscript. The authors vouch for the accuracy and completeness of the data and for the fidelity of the trial to the protocol.
We looked at the financial entanglements of these authors in part 1, but I think it’s worth repeating that the first two authors (the ones who helped design the study) had each taken hundreds of thousands of dollars from the companies that make the drugs being tested.
Also, they talk about the first draft of the manuscript being written by the first and last authors (and the thank you’s that I wrote about in part 1 mention an earlier draft.) Who wrote the final manuscript?
Their Background section states
Tirzepatide and semaglutide are highly effective medications for ob*sity management. The efficacy and safety of tirzepatide as compared with semaglutide in adults with ob*sity but without type 2 diabetes is unknown.
The idea of the drugs being “highly effective” is more marketing language than precise, scientific language - especially long-term. The idea that “the efficacy and safety of tirzepatide as compared with semaglutide is…unknown” is pure nonsense. I wrote about it in August of 2022. So either I’m Marty McFly, or something is fishy here. In truth, what they’ve done, essentially, is to replicate the approval trials for each drug. The main difference is that semaglutide’s original study was 68 weeks, so they’ve extended it a month to make it match Tirzepatide’s 72 weeks.
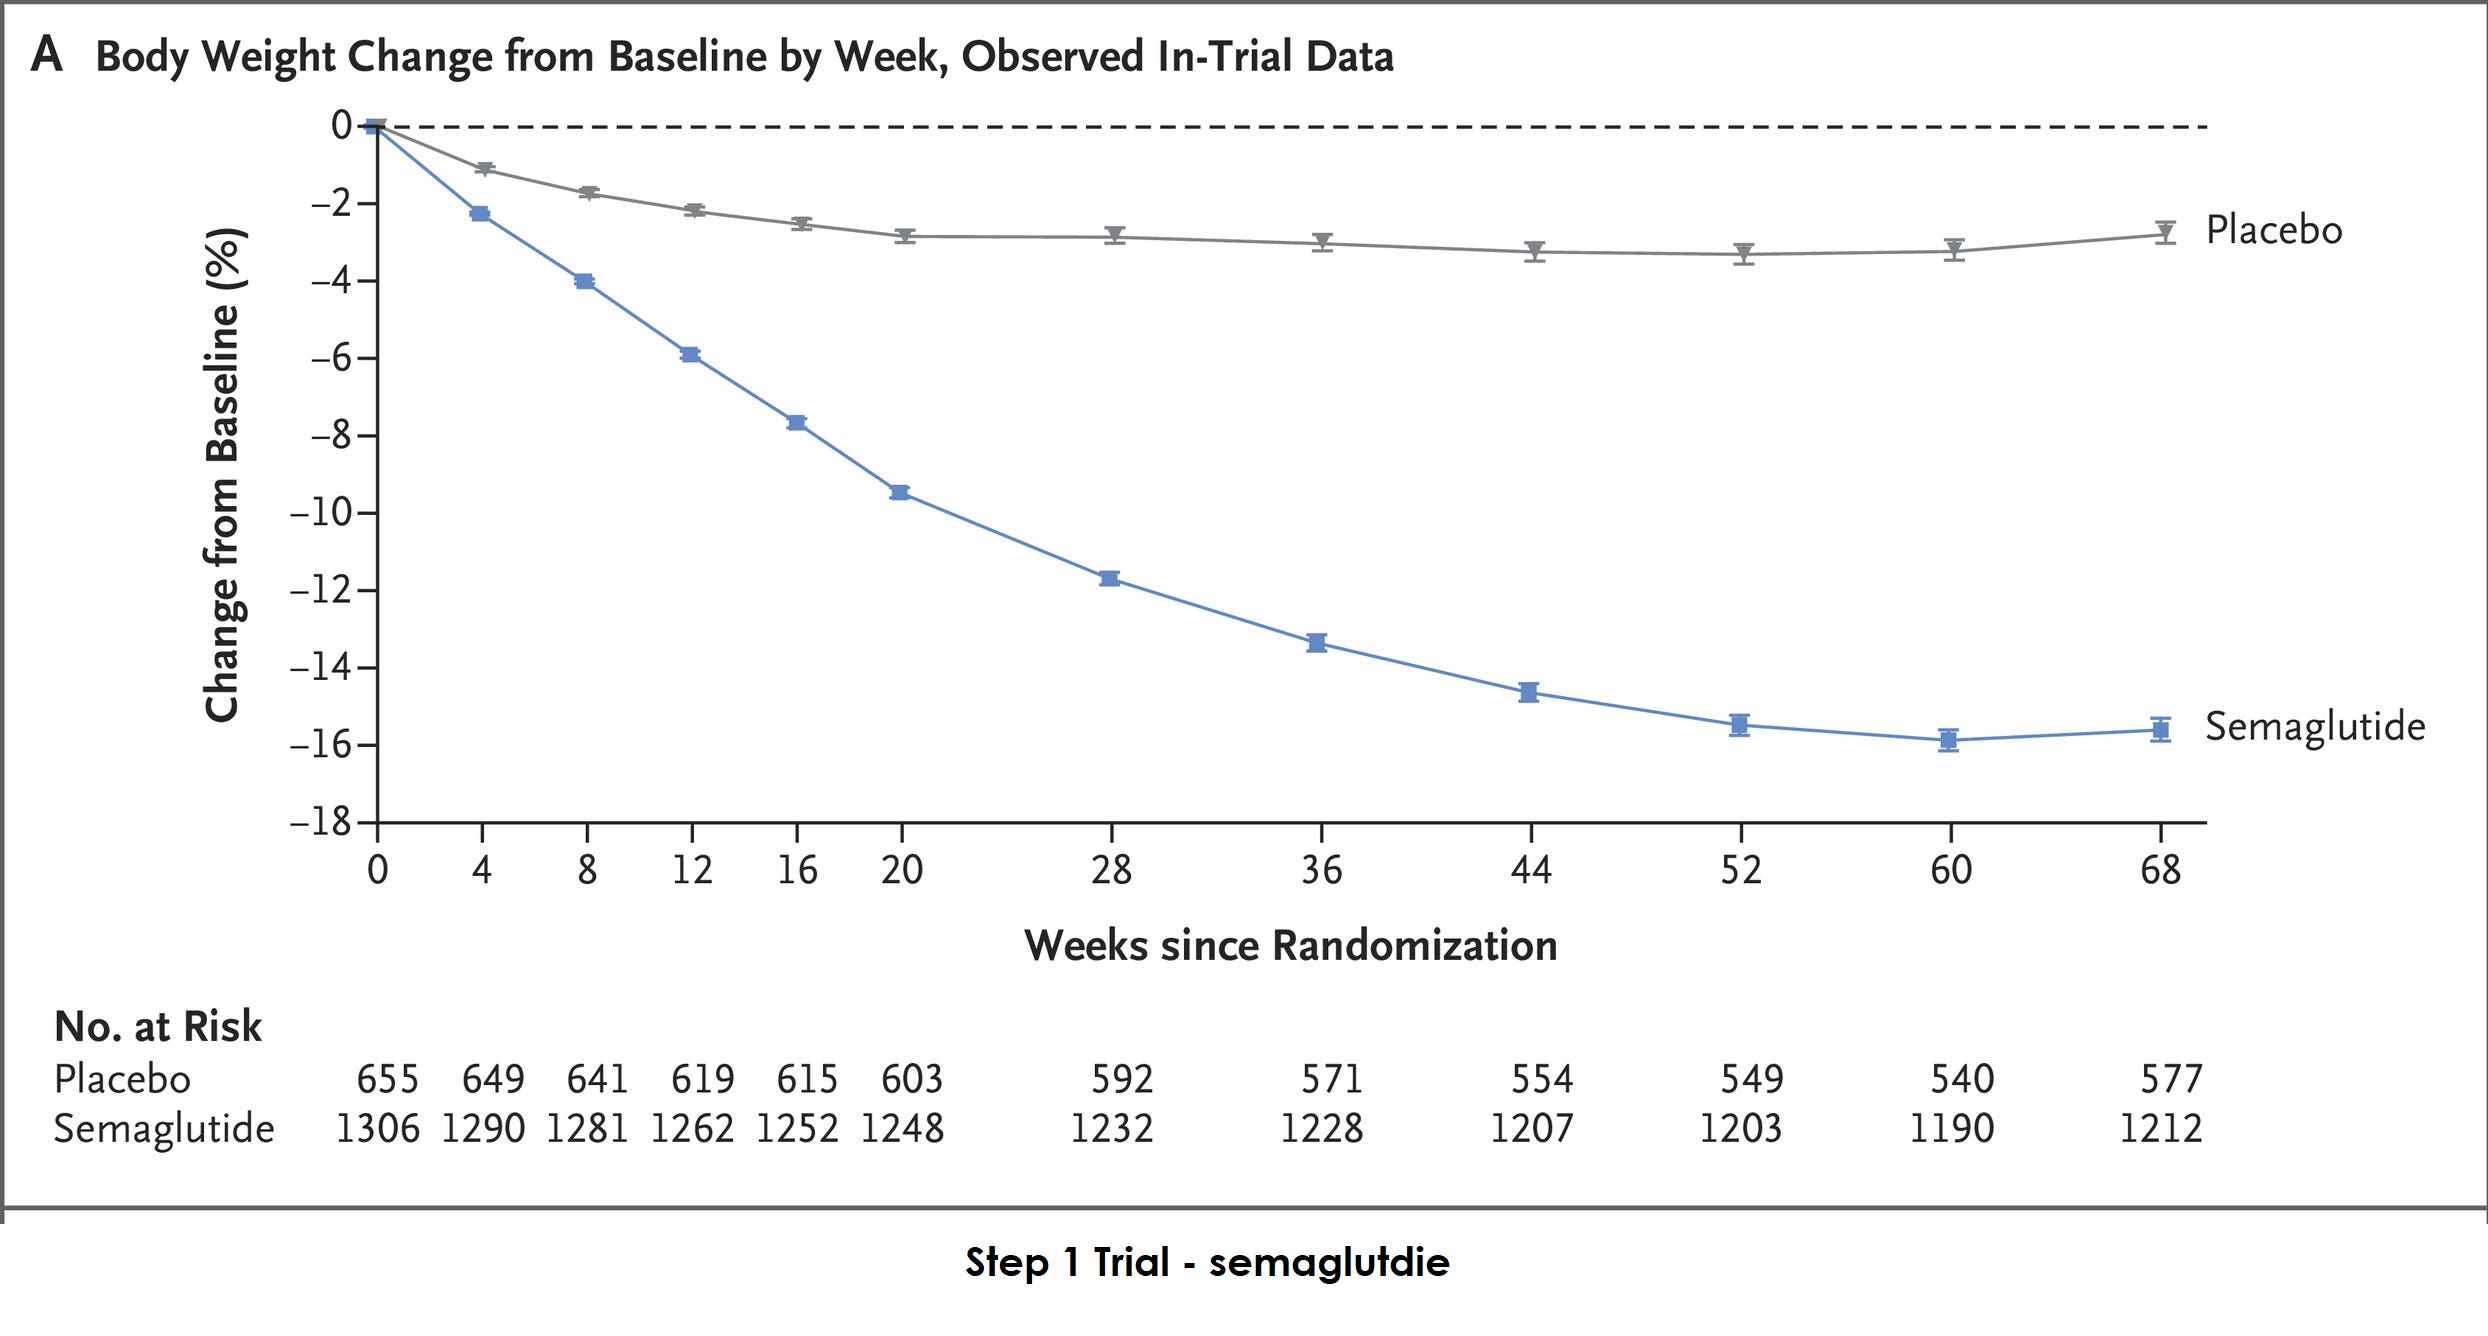
Here are the graphs from the original trials:
Semaglutide (Wegovy) STEP 1 Trial
Tirzepatide SURMOUNT 1 Trial
And here is the graph from this trial:

Maybe next they can develop a drug for sudden onset déjà vu.
Given that this research was already done, and given that this trial was initiated, paid for, and co-authored by employees of Eli Lilly, whose drug showed more weight loss in the initial trials, I’m forced to wonder if this is just an (incredibly expensive) publicity stunt. Did they do this whole thing just to get another round of press about how tirzepatide shows more weight loss than semaglutide? Besides the application of logic to the situation, there are a couple specific things that I think support this idea.
First, the duration. They could have chosen to use the original semaglutide trial duration of 68 weeks, saving time and money. But they already knew (because the studies have already been done!) that Semaglutide’s weight loss levels off around week 52 while tirzepatide’s doesn’t level off until around week 72, showing tirzepatide in its best light.
Also, this line from their statistical analysis feels like a smoking gun to me that this is more publicity stunt than important science
We estimated that a sample size of 700 participants (350 per group) would provide approximately 90% power to show that tirzepatide was superior to semaglutide with respect to the mean percent change in body weight from baseline to week 72. (emphasis mine)
In general, as someone who is part of several studies right now they don’t have funding and whose authors are all working in our free time without compensation to put important new information into the world, I understand and admit that these grapes are sour, but can I just suggest that instead of repeating (some of the most expensive types of ) existing trials, why not spend the money to get new information? Maybe longer term outcomes? (Or maybe not since Novo Nordisk’s 4-year results showed only 10% weight loss and that’s in the 10.5% of subjects they didn’t lose during the trial, but that’s just a guess on my part.) Or, hey, run a trial that compares actual health impacts of these drugs to weight-neutral interventions to see if the risk of the drugs is worth the reward.
I’m not going to do a line-by-line analysis of this trial since it’s just a replication of previous trials, but there is some interesting information here that I want to highlight.
First, the average weight loss was actually a bit less than in the original trials. They explain it:
Weight reduction was approximately 6% lower among men than among women in both treatment groups, a finding that is believed to explain the slightly lower weight reduction in the current trial than in previous trials. The current trial included a higher percentage of men (35%) than previous trials
Let’s break this down. The original trials over-represented cis-women (with no trans or nonbinary representation, which is a consistent, unacceptable problem within research.) The semaglutide trial was 76.1% cis-women and the tirzepatide trial was 67.6% in the 5mg group, 67.1% in the 10mg, and 67.5% in the 15mg group. Even this current trial still over-represents cis-women (65%). Cis-women, on average, experience weight loss that is approximately 6% higher than cis-men (at least short-term). This means that, whether intentionally or not, the average weight loss is boosted by consistently over-representing the group that loses more weight.
Here is another interesting line:
Both treatments decrease appetite and regulate food-related behaviors, presumably through expression of their respective receptor targets in subcortical regions of the brain that regulate food intake
Note the use of the word “presumably.” This is because these drugs have been found to cross the blood brain barrier, impacting the brain in ways that are not fully understood and with long-term impacts that are not fully known, especially at these high doses.
This one is…something:
Patient preferences are an essential component of shared decision making; however, older guidelines detailed patients’ weight-reduction goals as often not realistic and were from an era when available interventions led to weight reductions of only 5 to 10%.38 Recently, the OBSERVE study reported that adults with ob*sity may have weight-reduction goals of greater than 10%, especially those with class II and III ob*sity who have preferred weight-reduction goals of 20% or higher.39 In the study, the preferred weight reductions were not clinically excessive, given that approximately 85% of respondents were projected to continue to have ob*sity or overw*ight according to BMI after reaching their goal weight.38 Treatment that aligns with patient preferences may lead to increased adherence with better treatment outcomes.
Let’s take it bit by bit.
Patient preferences are an essential component of shared decision making
This is true, but it’s also complicated by the way that patient preferences (and provider recommendations) are often driven by marketing (sometimes in the form of “education” including grand rounds) from the weight loss industry. Further, patient-centered care must always be rooted in evidence-based medicine and informed consent, including informing patients not just of the risks and realities of these drugs, but also that there are weight-neutral options to support health directly rather than trying to manipulate body size.
However, older guidelines detailed patients’ weight-reduction goals as often not realistic37 and were from an era when available interventions led to weight reductions of only 5 to 10%.38
The citation here (38) is a paper from 1997 by Foster et al. called “What is a reasonable weight loss? Patients' expectations and evaluations of ob*sity treatment outcomes.” It’s actually fascinating and I’m planning to do a full piece on it, but for our purposes today, they found that the average participant’s weight loss goal was 32% body weight reduction. That is an amount of weight loss that neither of these drugs achieved so I’m not clear why they would intentionally cite that.
Recently, the OBSERVE study reported that adults with ob*sity may have weight-reduction goals of greater than 10%, especially those with class II and III ob*sity who have preferred weight-reduction goals of 20% or higher.
The “class” system of “ob*sity” is a beyond problematic, unscientific concept that I wrote about here. OBSERVE is a qualitative study conducted by Eli Lilly. It included phone surveys of 23 patient and 25 health care providers which concluded “both groups expressed interest in combining a new AOM with other weight management strategies to “kickstart” weight loss” AOM is an acronym for “Anti-Ob*sity Medication” with is a weight loss industry marketing phrase for weight loss drug.
In terms of the OBSERVE study, in general this type of small, qualitative study is a completely reasonable way to begin studying something if the goal is to determine if/what additional avenues of inquiry may be helpful for future studies. If someone is trying to claim conclusions that can be extrapolated and/or used in healthcare/public health practice, then that person (or company) would be well on their way to failing every undergraduate research methods class that exists.
Also, I didn’t do a deep dive for bias, but a study conducted by a company that sells weight loss medication concluding that patients and providers want patients to take… wait for it…weight loss medication is a red flag. Further, doctors and patients might like the idea that these meds can be used to “kick start” weight loss, but the possibility is refuted by the actual research which has consistently found rapid weight regain after ceasing the drugs.
In the study, the preferred weight reductions were not clinically excessive, given that approximately 85% of respondents were projected to continue to have ob*sity or over*eight according to BMI after reaching their goal weight.38
This is such obtuse phrasing that I read it a few times. It reminds me of a term paper written by an undergrad who skipped both the lectures and the reading material and is throwing the paper together the night before. What I’m reading is that, in the Foster study, even if the respondents lost as much as weight as their stated goal (which is more weight loss than either tirzepatide or semaglutide produced in this trial) a whopping 85% of them would still be “overw*ight” or “ob*se”.
To be clear, I argue that there is nothing wrong with being higher-weight. The truth is that these labels were created for the express purpose of pathologizing bodies based on shared size rather than shared symptomatology or cardiometabolic profile like we would see in an actual disease diagnosis, which I’ve written about in detail. The construct of higher weight (aka “overw*ight” or “ob*se”) being considered a health issue/disease has been predominantly architected by the weight loss industry, including the companies that peddle these drugs. They seem to be admitting here that, for the vast majority of people, these drugs are not a “cure” for the “disease” they made up.
Treatment that aligns with patient preferences may lead to increased adherence with better treatment outcomes.
Again, “patient preferences” is a bit of a loaded term when patient experiences include being misled (including by healthcare providers) that weight loss is their only path to health and/or having other healthcare (like surgical procedures) held hostage for a weight loss ransom. Also, the use of “may lead” shows how they are stretching here.
They also claim that
higher categorical weight reductions were associated with greater improvements in each cardiometabolic risk factor
But before we can credit these drugs or, separately, the weight loss they produce (at least short-term) with cardiometabolic risk factor improvements, there are questions to ask. For example, separately they explain that:
All the participants received counseling on nutrition and physical activity.
And that’s the thing. It’s possible that improvements in cardiometabolic risk factors could have come from behavior changes. In their 2021 study, Gaesser and Angadi found that “most cardiometabolic risk markers associated with ob*sity can be improved with exercise training independent of weight loss and by a magnitude similar to that observed with weight-loss programs”
The idea that higher amounts of weight loss were associated with greater health improvements can easily be read as “this proves that the health improvements are due to the weight loss” but that is far from the case. There are a lot of other possibilities as well. It could be a chicken and egg situation. It could also be that the belief that weight loss/being thinner makes someone better, may mean that as they lose weight (at least short term) these participants now see their bodies as more worthy of care and are thus participating in more health supporting behaviors. Or it could be that as they become thinner, people feel more worthy to take up space in the world and/or are better accommodated, for example in fitness spaces. Their stress may be decreased, they may be more inclined to make social connections, all of which can impact health.
However, we don’t know if the weight loss will last long term and while individuals have a right to make decisions for themselves, a healthcare system that suggests that the solution to the physical, mental, and social impacts of weight stigma is for higher-weight people to risk their lives and quality of life to change themselves to escape oppression is a healthcare system that is headed down a dangerous road.
We don’t need more short-term studies of these weight loss drugs. What is desperately needed are studies that compare these drugs (and other weight loss methods) to weight-neutral interventions that focus on supporting health directly to see if they create similar (or greater) benefits (especially long-term) with fewer risks.
Did you find this post helpful? You can subscribe for free to get future posts delivered direct to your inbox, or choose a paid subscription to support the newsletter (and the work that goes into it!) and get special benefits! Click the Subscribe button below for details:
Liked the piece? Share the piece!
More research
The Research Post
More resources
The Resource Post
*Note on language: I use “fat” as a neutral descriptor as used by the fat activist community, I use “ob*se” and “overw*ight” to acknowledge that these are terms that were created to medicalize and pathologize fat bodies, with roots in racism and specifically anti-Blackness. Please read Sabrina Strings’ Fearing the Black Body – the Racial Origins of Fat Phobia and Da’Shaun Harrison’
Ragen, I love this newsletter. Your sharp eye and even sharper wit always get me — this line: “Maybe next they can develop a drug for sudden onset déjà vu.” Pure gold. Such a perfect jab at the endless whack-a-mole game these drug companies are playing. Thank you for all you do!
Thank you so much Ragen, your expertise and insights and invaluable! A question I had (and I apologize if you’ve addressed this before)…I’m curious about the eventual tapering of weight loss in the studies. At some point weight loss will taper off because there is no more weight to lose. Is it possible that is why the weight loss eventually slows and the curve flattens?